Vitamins That Remove Plaque From Arteries: What the Evidence Actually Shows

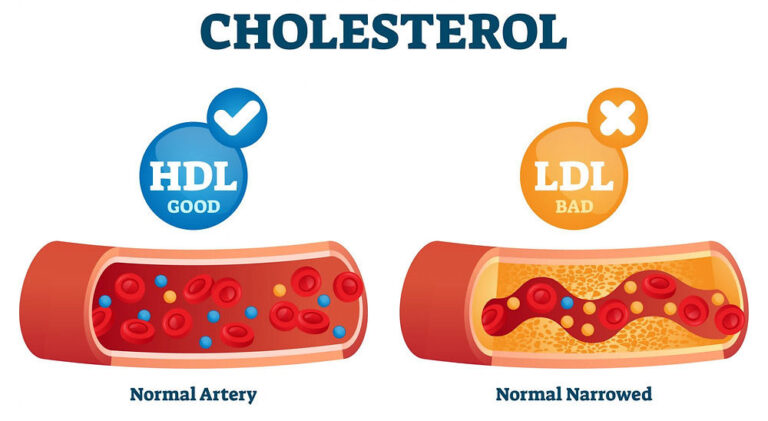
Vitamins that remove plaque from arteries — the claim appears regularly in supplement marketing. The honest clinical answer is more nuanced: no vitamin dissolves or removes existing plaque. But several vitamins and nutrients have robust evidence for slowing plaque progression, reducing the oxidative and inflammatory processes that drive atherosclerosis, and in some cases directly supporting arterial wall health. This guide covers what the evidence actually shows, at what doses, and which patients benefit most.
Vitamin K2 is the most clinically important vitamin for arterial health, though it remains poorly understood outside integrative medicine.
The D3+K2 combination, magnesium, and omega-3s are the starting point for most patients — but the precise protocol depends on what the testing reveals.
Vitamins and Nutrients With Evidence for Arterial Health
1. Vitamin K2 (MK-7 Form) — The Artery Calcification Vitamin
Vitamin K2 is the most clinically important vitamin for arterial health, though it remains poorly understood outside integrative medicine. Its primary cardiovascular mechanism is activation of Matrix Gla Protein (MGP) — a protein that prevents calcium from depositing in arterial walls. When K2 levels are insufficient, MGP remains inactive and calcium migrates into soft tissues including arteries, driving arterial stiffening and calcification (the primary component of “hardening of the arteries”).
The Rotterdam Study — a landmark Dutch population study — found that participants with the highest dietary vitamin K2 intake had a 52% lower risk of severe aortic calcification and 57% lower cardiovascular mortality compared to those with the lowest intake. The MK-7 form of vitamin K2 has the longest half-life (72 hours versus 1 hour for MK-4), providing more sustained MGP activation. Standard dose: 90–180 mcg daily of MK-7. Patients on warfarin must consult their physician before supplementing with any form of vitamin K.
What the 2026 DANCODE trial added. Until recently the case for K2 rested largely on observational studies. In August 2026, researchers presented DANCODE at the European Society of Cardiology Congress and published it in Circulation: 398 people with severe coronary calcification took either 720 mcg of vitamin K2 with 1,000 IU of vitamin D3, or a placebo, for two years. The supplement group’s calcium scores rose 21% more slowly than the placebo group’s.
Read that carefully, because it is easy to over-read. Calcium scores still went up in both groups — this was slower accumulation, not plaque removal. Total plaque and soft plaque, the kind most linked to heart attacks, did not change. And while a calcium score is a well-established predictor of cardiac risk, a slower rise in that score has not been shown to mean fewer heart attacks — so the study’s authors state plainly that it “does not establish a role for routine vitamin K2 and D3 supplementation.” The accompanying editorial concluded these vitamins should not be prioritised over, or substituted for, treatments already proven to prevent cardiac events. The trial was funded by a vitamin K2 manufacturer, though the company had no role in its analysis.
It is a genuine and encouraging mechanistic finding. It is not proof that supplements clear arteries.
2. Vitamin D3 — Vascular Tone and Inflammation
Vitamin D receptors are expressed throughout the cardiovascular system — including in endothelial cells, vascular smooth muscle, and cardiac myocytes. Deficiency (defined as serum 25-OH-D below 20 ng/mL, which affects over 40% of US adults) is associated with hypertension, increased arterial stiffness, elevated inflammatory markers, and higher cardiovascular event rates. Vitamin D reduces renin production (lowering blood pressure), modulates macrophage function (reducing plaque inflammation), and improves endothelial function. Standard replacement dose: 2,000–5,000 IU daily of D3, ideally with K2 (D3 promotes calcium absorption, K2 directs it to bones rather than arteries — the two work synergistically). Dose should be guided by 25-OH-D blood levels.
One nuance worth knowing: vitamin D’s relationship with arterial calcification is U-shaped, meaning both too little and too much appear unhelpful. The DANCODE trial paired K2 with just 1,000 IU of D3 — a modest dose, and lower than the range most often recommended for correcting a deficiency. More vitamin D is not automatically better, which is why dosing is guided by a 25-OH vitamin D blood level rather than by a number on a bottle.
Reading the label: mcg vs IU. Studies and supplement bottles often speak in different units. For vitamin D, one microgram equals 40 IU — so the 25 mcg used in the DANCODE trial is the same as 1,000 IU on a label. Vitamin K2 is different: it has no IU value at all and is only ever measured in micrograms.
The trial’s regimen was high in K2 and low in D3 — the opposite of most combination capsules. Reaching its 720 mcg of K2 by taking eight typical K2-D3 capsules would also mean 40,000 IU of vitamin D a day, far above a safe intake. A research dose is not a recommendation, and it is never something to reach by stacking capsules.
See the full dose comparison in our Vitamin K2 + D3 guide.
3. Magnesium — The Overlooked Vascular Mineral
Magnesium is not technically a vitamin but is the most commonly deficient micronutrient in patients with cardiovascular disease, and its vascular effects are profound. Magnesium acts as a natural calcium channel blocker — it relaxes vascular smooth muscle, reducing blood pressure and arterial stiffness. Low intracellular magnesium is associated with increased arterial calcification, endothelial dysfunction, platelet hyperactivity, and arrhythmia susceptibility. Standard serum magnesium testing misses intracellular deficiency — Dr. Druz uses RBC magnesium for accurate assessment. Standard supplemental dose: 200–400 mg daily of magnesium glycinate or malate (better tolerated than magnesium oxide).
4. Omega-3 Fatty Acids (EPA and DHA)
Omega-3 fatty acids are the most extensively studied cardiovascular supplements with the strongest outcomes data. EPA and DHA reduce triglycerides by 20–50% at therapeutic doses, lower inflammatory markers (IL-6, hsCRP), reduce platelet aggregation, and improve endothelial function. The REDUCE-IT trial demonstrated that high-dose EPA (4 grams daily) reduced major cardiovascular events by 25% in high-risk statin-treated patients with elevated triglycerides. Therapeutic cardiovascular dose: 2–4 grams daily of combined EPA+DHA. Quality matters — choose products with third-party testing for oxidation and heavy metals.
5. Coenzyme Q10 (CoQ10) — Mitochondrial Support and LDL Protection
CoQ10 is an endogenous antioxidant critical for mitochondrial energy production in heart muscle and for protecting LDL from oxidation — the initiating step in atherosclerotic plaque formation. Statins deplete CoQ10 by inhibiting the mevalonate pathway, and many of the muscle symptoms attributed to statins are believed to be at least partially driven by CoQ10 depletion. Clinical trials show CoQ10 reduces systolic blood pressure by approximately 11 mmHg and diastolic by approximately 7 mmHg. Standard dose: 100–400 mg daily; the ubiquinol form has superior absorption, particularly in patients over 50.
6. Vitamin C — Endothelial Protection and Collagen Synthesis
Vitamin C is the primary water-soluble antioxidant in plasma and plays a specific role in cardiovascular health by regenerating oxidized vitamin E, supporting endothelial nitric oxide production, and reducing LDL oxidation. It is also essential for collagen synthesis — the structural protein that maintains arterial wall integrity. Epidemiological studies consistently show inverse associations between vitamin C status and cardiovascular disease. Standard cardiovascular dose: 500–1,000 mg daily of ascorbic acid or buffered vitamin C. Unlike fat-soluble vitamins, excess vitamin C is excreted and toxicity is rare.
When to See a Doctor About Vitamins and Arterial Health
Vitamin supplementation for arterial health should be guided by testing, not guesswork. The most clinically important tests before starting a cardiovascular vitamin protocol include 25-OH vitamin D, RBC magnesium, omega-3 index, CoQ10 levels (particularly in statin users), and coronary artery calcium scoring to assess actual plaque burden. Supplementing without knowing your baseline levels risks both under-dosing (no clinical effect) and over-dosing (vitamin D toxicity, for example, can cause hypercalcemia).
The Integrative Cardiology Approach
At Holistic Heart Centers, vitamin and nutrient optimization is part of a comprehensive cardiovascular protocol — not a generic supplement stack. Dr. Druz assesses each patient’s deficiency profile, arterial health status (including CAC scoring), and medication list before recommending specific nutrients at specific doses. The D3+K2 combination, magnesium, and omega-3s are the starting point for most patients — but the precise protocol depends on what the testing reveals.
Want to know which vitamins are right for your arterial health?
A Step 1 Explore visit with Dr. Druz includes comprehensive micronutrient assessment alongside advanced lipid and arterial imaging.
Schedule a free strategy call →Top Vitamins for Arterial Health
These statements have not been evaluated by the Food and Drug Administration. Supplements are not intended to diagnose, cure, or treat any disease, and are not a substitute for appropriate cardiovascular evaluation with a qualified healthcare professional.
Medically reviewed by Dr. Regina Druz, MD, MBA, FACC, FMCP-M — Board-Certified Integrative Cardiologist at Holistic Heart Centers, Roslyn, NY. Last reviewed: August 2026.
References
- Geleijnse JM, et al. Dietary Intake of Menaquinone Is Associated with a Reduced Risk of Coronary Heart Disease. J Nutr. 2004;134(11):3100-3105.
- Hasific S, et al. Vitamin K2 and D3 Supplementation in Patients With Severe Coronary Artery Calcification: The DANCODE Trial. Circulation. 2026;154.
- Daubert MA, Blaha MJ. Coronary Calcium Regression With Vitamin Supplementation: A Therapeutic Target or Too Good to be True? Circulation. 2026;154.
- Bhatt DL, et al. Cardiovascular Risk Reduction with Icosapentaenoic Acid (REDUCE-IT). N Engl J Med. 2019;380(1):11-22.
- Rosenfeldt FL, et al. Coenzyme Q10 in the Treatment of Hypertension. J Hum Hypertens. 2007;21(4):297-306.
- Holick MF. Vitamin D Deficiency. N Engl J Med. 2007;357(3):266-281.
More Articles on Heart Disease
-
Can Diet Reverse Heart Disease?
Read more →: Can Diet Reverse Heart Disease?Heart Disease Diet can contribute to reversing heart disease, particularly when it addresses the root causes of atherosclerosis like inflammation, insulin resistance, and oxidative stress. Clinical trials have demonstrated measurable plaque regression with intensive dietary intervention. However, diet alone may not be sufficient for everyone, especially those with advanced disease, genetic risk factors, or significant…
-
What Causes Heart Disease?
Read more →: What Causes Heart Disease?Heart Disease Heart disease is caused by damage to the blood vessels and heart muscle that accumulates over time. While cholesterol often receives the most attention, the actual disease process is driven by a combination of chronic inflammation, metabolic dysfunction, oxidative stress, and arterial damage. These factors interact to create atherosclerosis, the buildup of plaque…
-
Why Is Heart Disease The Leading Cause Of Death?
Read more →: Why Is Heart Disease The Leading Cause Of Death?Heart Disease Heart disease remains the leading cause of death worldwide because it develops silently over decades, is driven by common modern lifestyle factors, and is often detected too late requiring invasive intervention. The cardiovascular system is uniquely vulnerable to the cumulative effects of inflammation, metabolic dysfunction, and arterial damage. Unlike many other diseases, heart…
See all Heart Disease articles → | Back to Heart Health Blog